

Clinicians and Trials Agree on Myotherapy Benefits
Myotherapy can reduce musculoskeletal pain and improve mobility, with meta-analyses and randomized trials backing measurable gains in pain scores and physical function. The strongest support comes from work on chronic low back pain and general manual therapy outcomes, though evidence certainty varies by condition and study quality. This guide walks through what the research shows, which conditions respond best, and what a realistic course of treatment looks like.
TL;DR:
- Multiple sessions paired with active rehabilitation are necessary for myotherapy to produce sustained pain relief, especially in chronic conditions.
- Myotherapy shows the strongest evidence for improving low back pain, neck tension, and sports injuries involving soft tissue restrictions.
- Immediate physiological effects include increased blood flow and tissue oxygenation, which support the biological plausibility of pain reduction.
- Effect sizes for pain and function improvements are modest, and long-term benefits remain uncertain without consistent follow-up and movement therapy.
- Candidates should focus on ongoing exercise and self-care strategies, as passive treatments alone tend to diminish quickly after sessions.
Table of Contents
- 1. Top therapeutic benefits of myotherapy
- 2. Conditions and complaints myotherapy commonly treats
- 3. How myotherapy works: plausible mechanisms
- 4. What the evidence says about pain and function outcomes
- 5. What to expect from treatment: sessions, frequency, and risks
- 6. Who is a good candidate and who should be cautious
- 7. Practitioner perspective: how a clinical model shapes results
- 8. What this evidence means for how you should approach treatment
- 9. Getting started with hands-on treatment in Plano
- Sources
- FAQ
1. Top therapeutic benefits of myotherapy
Myotherapy blends trigger-point work, myofascial release, and structured rehabilitation into a single hands-on approach. The benefits reported across clinical literature cluster around a few consistent themes.
- Pain reduction: Patients with low back pain, neck pain, and localized trigger-point pain often report measurable drops in pain scores after treatment.
- Improved mobility: Stiff joints and tight muscle groups tend to regain range of motion once fascial and muscular restrictions ease.
- Reduced muscle tension: Deactivating trigger points lowers the baseline tightness that drives many chronic aches.
- Better circulation to soft tissue: Hands-on techniques appear to increase local blood flow and oxygen delivery to treated tissue.
- Secondary stress and sleep benefits: Some patients report calmer nervous systems and better sleep after sessions, likely tied to the broader relaxation response.
A 2026 meta-analysis of many studies covering several thousand participants found manual therapy reduced pain and lowered anxiety scores on validated scales compared to controls, according to research published in Frontiers in Psychology. That combination of physical and psychological effects is unusual for a purely mechanical intervention, and it suggests myotherapy’s benefits extend past the treated tissue itself.
Not every benefit holds up equally well under scrutiny. A broad mapping review of massage therapy trials found many studies but generally low-to-moderate certainty of evidence overall, with only a minority of conclusions reaching moderate certainty for pain outcomes. The takeaway is not that myotherapy fails to help. It is that the size and durability of that help vary by condition, technique, and how many sessions a patient completes.
2. Conditions and complaints myotherapy commonly treats
Myotherapy tends to work best on musculoskeletal complaints tied to soft tissue dysfunction rather than structural damage or systemic disease. The list below covers the conditions that show up most often in clinical practice and in the trial literature.
- Chronic low back pain: Myofascial components of low back pain, including tight thoracolumbar fascia and paraspinal trigger points, respond to targeted release work.
- Neck pain and cervicogenic headaches: Tension patterns in the upper trapezius and suboccipital muscles often refer pain into the head, and releasing them can ease headache frequency.
- Sports and overuse injuries: Hamstring strains, plantar fasciitis, and various tendinopathies frequently involve fascial restriction alongside the primary injury.
- Entrapment and repetitive strain conditions: Carpal tunnel symptoms sometimes improve when forearm and wrist fascia is addressed, though results are more variable than for spinal complaints.
In most of these cases, myotherapy works as one piece of a larger plan rather than a standalone fix. A therapist releasing a tight calf will usually pair that work with corrective exercise for the ankle or hip mechanics that caused the tightness in the first place. That combination, hands-on treatment plus movement correction, shows up repeatedly in the research as the pattern most associated with lasting improvement rather than short-term relief that fades within days.
3. How myotherapy works: plausible mechanisms
Myotherapy’s effects likely come from several overlapping pathways rather than one single mechanism. Understanding them helps set realistic expectations about what a session can and cannot do.
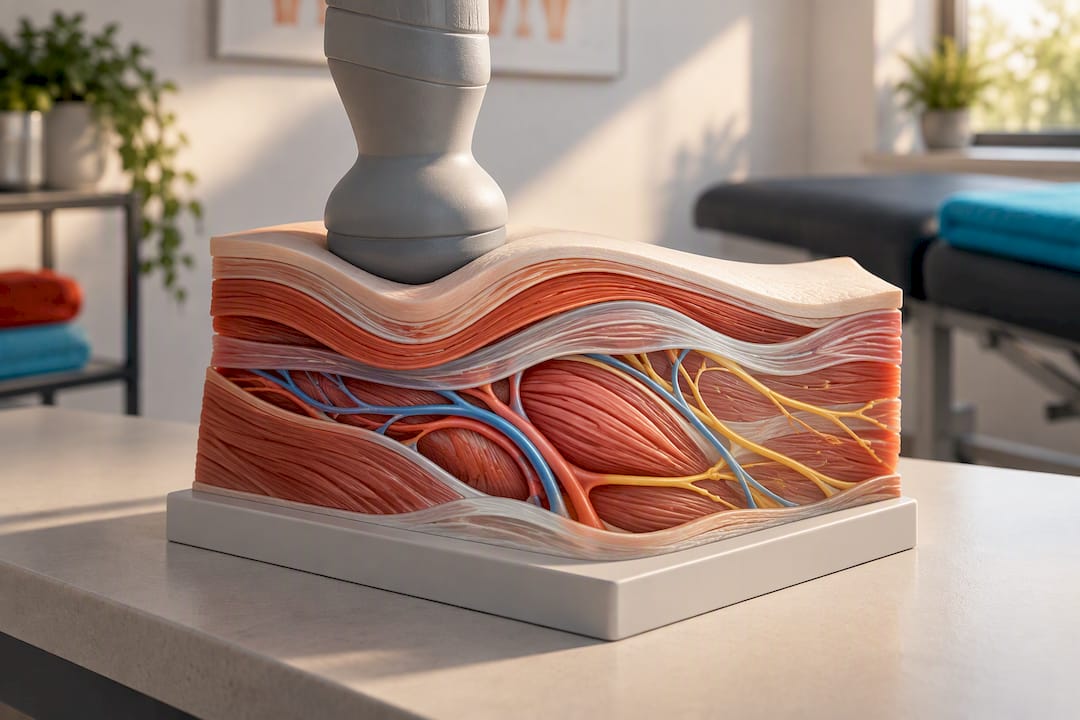
The most direct mechanism is mechanical: sustained pressure and stretching on fascia and muscle tissue can change tissue length and reduce localized tension. Circulatory changes appear to matter too. Randomized trials measuring lumbar tissue after myofascial release found blood flow increased by roughly 31.6% immediately after treatment and by 48.7% at a 60-minute follow-up compared to placebo, according to a 2023 physiologic trial. That kind of measurable change in blood flow and oxygenation gives hands-on techniques a plausible biological pathway beyond simple relaxation.
Neuromodulation likely plays a role as well. Trigger-point work and myofascial techniques appear to alter local muscle recruitment patterns and may influence central pain processing, not just the tissue under the therapist’s hands. A 2024 review from an international pain research taskforce describes manual therapy’s effects as mediated through a mix of biomechanical, neurological, and neurovascular pathways, with evidence generally rated low to moderate across the conditions studied.
Contextual factors matter too. The therapeutic relationship, patient expectation, and the ritual of a structured session all likely contribute something to the outcome, which is common across manual therapies and not unique to myotherapy. This is part of why integrating manual work with active exercise matters: passive treatment alone rarely produces changes that outlast the tissue effects of a single session.
4. What the evidence says about pain and function outcomes
The clearest data on myotherapy’s specific techniques comes from research on myofascial release for chronic low back pain. A systematic review and meta-analysis of eight randomized controlled trials involving 375 patients found significant improvements in pain, with a standardized mean difference of negative 0.37, and physical function, with a standardized mean difference of negative 0.43. The same analysis found no significant effect on quality of life or trunk mobility, which is a useful reminder that myotherapy tends to help specific outcomes rather than everything at once.
Manual therapy broadly reduced pain scores by 16.01 points and anxiety scores by 9.68 points in the 2026 meta-analysis covering nearly 5,500 participants, reinforcing that the pain-relief effect is not limited to one technique or one body region.
A few caveats shape how much weight these numbers should carry:
- Heterogeneity: Trials vary widely in technique, dosage, and patient population, which makes pooled effect sizes approximate rather than precise.
- Small sample sizes: Many individual trials involve fewer than 50 participants, which limits statistical power.
- Short follow-up periods: Most studies measure outcomes at a few weeks or months, so long-term durability is less clear.
The practical interpretation: myotherapy is more likely to produce short- to medium-term relief than a permanent fix on its own, and combining it with active rehabilitation gives those gains a better chance of sticking.
5. What to expect from treatment: sessions, frequency, and risks
A typical myotherapy visit starts with an assessment of movement patterns and painful areas, followed by hands-on work such as trigger-point pressure or myofascial release, and usually ends with a home exercise prescription. Most clinics follow a similar general arc:
- Initial phase: Weekly sessions for the first few weeks while acute pain and restriction are highest.
- Tapering phase: Sessions spread out to every two to three weeks as mobility improves and home exercises take over more of the workload.
- Maintenance phase: Occasional sessions as needed, often tied to activity spikes like a new training block or a physically demanding work period.
Short-term responses, such as reduced tightness right after a session, are common and expected. Sustaining those gains generally depends on whether the patient keeps up with prescribed movement work between visits, since passive treatment alone tends to fade faster than treatment paired with active rehab.
Mild soreness, temporary bruising, or fatigue in the treated area are common and typically resolve within a day or two. Red flags that warrant stopping treatment and seeking medical evaluation include sudden severe pain, numbness that spreads or worsens, fever, or unexplained weight loss alongside pain, since these can signal something beyond a soft tissue issue.
Pro Tip: Track your pain on a simple 0-to-10 scale and note your range of motion for a key movement before starting treatment, then recheck weekly. That gives you an objective way to judge whether sessions are actually working rather than relying on memory.
6. Who is a good candidate and who should be cautious
Myotherapy tends to suit people dealing with musculoskeletal pain linked to soft tissue dysfunction, tight muscles, or trigger points, especially when there is no sign of fracture, active infection, or systemic illness. Results tend to be best when treatment is paired with an exercise or activation component rather than used as a passive fix.
- Good candidates: People with chronic low back or neck pain, tension headaches, or overuse injuries without red-flag symptoms.
- Use caution or seek clearance first: Anyone with a suspected fracture, active infection, unexplained systemic symptoms, or a recent acute injury with significant swelling.
- Ask your provider: What technique they plan to use, how many sessions they expect before reassessing progress, and whether they will prescribe home exercise alongside hands-on work.
A short pre-visit checklist, noting your main pain locations, what makes symptoms better or worse, and any recent injuries, helps a practitioner build a more targeted plan from the first appointment.
7. Practitioner perspective: how a clinical model shapes results
Some chiropractic clinics in Plano, Texas, use the Fascial Distortion Model, a hands-on approach that targets specific types of soft tissue distortion rather than treating pain as a generic symptom. This approach may be paired with focused shockwave modalities and myofascial release techniques within individualized plans built around detailed assessments of movement and biomechanics.
That assessment step matters because two patients with the same complaint, say plantar fasciitis, can have different underlying restrictions driving it. Some clinics have reported cases where myofascial-focused care contributed to improvement in conditions such as sciatica and plantar fasciitis, framed as outcomes seen in their own patient base rather than as a universal guarantee. Readers considering myofascial release sessions or muscle activation therapy can find more detail on how these techniques are structured in practice.
8. What this evidence means for how you should approach treatment
The research supports a fairly narrow but useful conclusion: myotherapy techniques can meaningfully reduce pain and improve function for specific conditions, particularly chronic low back pain, but they are not a universal or permanent solution on their own. The conventional pitch you often hear, that a few sessions of hands-on work will resolve chronic pain, overstates what the trial data actually shows.
What gets underrated is the role of dosage and follow-through. A single-session crossover trial testing one round of myofascial release for chronic low back pain found no significant change in pain or disability scores, which tells you that one appointment rarely moves the needle. The trials that do show benefit generally involve multiple sessions paired with some form of active rehabilitation.
If you take one thing from this, prioritize consistency and follow-up exercise over chasing a single miracle session. Hands-on work sets the stage. What you do with your body between appointments is what determines whether the relief holds.
— Chris
9. Getting started with hands-on treatment in Plano
If you are dealing with pain that has not responded to stretching or rest, hands-on treatment paired with a structured plan tends to outperform either approach alone. The Tx Room’s Chiropractic Care and Soft Tissue Therapy combine assessment-driven manual work with rehabilitation, using the same techniques discussed throughout this guide.
- For chronic low back or fascia-related tightness: Myofascial release sessions target the tissue restrictions covered in the evidence above.
- For tendon or overuse injuries: Deep Tissue Therapy Laser and Dry Needling address localized irritation and trigger points.
- For stubborn cases that have not responded to standard care: MyACT focused shockwave therapy offers an additional option built on the same fascial framework.
A first visit typically includes a movement assessment and a discussion of your pain history, so bring notes on when symptoms started and what has helped or worsened them. You can check availability and book directly through The Tx Room’s main page.
Sources
For readers who want to look at the underlying research directly, a few sources stand out. The 2026 Frontiers meta-analysis covers the broadest set of outcomes across nearly 90 studies. The myofascial release meta-analysis for chronic low back pain offers the clearest condition-specific effect sizes. The massage therapy mapping review gives useful context on how much certainty exists across the field as a whole, and the blood flow and oxygenation trial grounds the mechanism in measurable physiology. Readers dealing with cyclical or menstrual-related back pain may also find practical guidance on nonpharmacologic relief useful as a complementary resource.
- Effectiveness of manual therapy on physical and mental health promotion in adults: a systematic review and meta-analysis (Frontiers, 2026)
- Use of Massage Therapy for Pain, 2018-2023: A Systematic Review
FAQ
How often should you see a myotherapist?
Most treatment plans start with weekly sessions for the first few weeks, then taper to every two to three weeks as symptoms improve. A single session rarely produces lasting change, since trial data on one-time myofascial release found no significant improvement in pain or disability scores.
How is myotherapy different from massage?
Myotherapy focuses specifically on trigger-point deactivation and corrective exercise rather than general relaxation, using structured techniques like ischemic pressure and myofascial release. General massage can share some techniques but usually lacks the same emphasis on assessment-driven, condition-specific treatment plans.
Why does myofascial release feel so good?
Myofascial release appears to increase blood flow and tissue oxygenation almost immediately, which likely contributes to the sense of relief patients report. Research measuring lumbar tissue found blood flow increased by about 31.6% right after treatment, an effect documented in a 2023 physiologic trial.
What is the difference between a myotherapist and a chiropractor?
A myotherapist focuses on soft tissue techniques such as trigger-point work and myofascial release, while a chiropractor typically emphasizes joint alignment and spinal manipulation, sometimes alongside soft tissue methods. Many clinics, including those using the Fascial Distortion Model, blend both approaches into a single treatment plan targeting soft tissue and biomechanical issues together.